Breast augmentation is one of the most frequently performed aesthetic operations in the world, and one of the most frequently misunderstood. Done well, it is not about making breasts as large as possible. It is about proportion: choosing an implant, a plane and a technique that fit your chest, your tissue and your life, so that the result looks like it belongs to you. This page explains how I approach breast augmentation in Istanbul for international patients, what an honest consultation covers, and what you should know before you travel.
Who breast augmentation is for
Patients come to breast enlargement surgery from different starting points. Some have always had small breasts relative to their frame. Some have lost volume after pregnancy, breastfeeding or significant weight loss, where the upper pole of the breast empties and the skin envelope loosens. Some have a visible asymmetry they have managed with padding for years. The operation addresses volume and shape; it does not by itself lift a significantly sagging breast, and part of an honest assessment is telling you when what you actually need is a lift, a lift with implants, or a combined plan such as a mommy makeover rather than an implant alone.
Boob Job, Breast Implants, Round or Teardrop, Hybrid: What the Words Mean
The vocabulary around breast augmentation is a mix of slang, brand language and genuine clinical distinctions, and a few of the words change what operation you are actually asking for. What each one means in my practice:
- Boob job, breast enlargement, breast augmentation, augmentation mammoplasty. The same operation. “Boob job” is what most UK patients type into a search engine; “augmentation mammoplasty” is what appears on the consent form.
- Breast implants versus fat transfer. Implants add predictable volume in one step. If you want no implant at all, augmentation with your own fat alone is possible when there is enough donor fat; the gain is modest, roughly half a cup to one cup per session. For a clear size change the implant is the tool; fat is the refinement or, by choice, the alternative.
- Round versus teardrop (anatomical) implants. Round implants give fullness in the upper pole and cannot rotate into a wrong position. Teardrop implants mimic the natural slope but can rotate and need a textured surface to stay put. I use round implants in most augmentations, because the “teardrop look” comes from the plane, the profile and the patient’s own tissue rather than from the shape of the device; if you prefer a teardrop implant, I use one, and we discuss the trade-offs.
- Profile: low, moderate, high. How far an implant projects forward for a given width. A narrow chest usually needs a higher profile to reach the same volume; a broad chest takes a wider, lower implant. Profile, not volume, is where most of the fine tuning happens.
- Cup size and cc. There is no fixed conversion. As a rough rule of thumb, 150 to 200 cc changes one cup size, but the same 300 cc implant is a modest change on a broad frame and a dramatic one on a narrow frame. I size by base width and tissue, then show you the result with sizers: how implant size is actually chosen.
- Micromastia, small breasts, breast hypoplasia. Medical terms for underdeveloped breast volume, the most common reason for augmentation in younger patients.
- Tubular (tuberous) breasts. A developmental shape with a narrow, constricted base, a high fold and a puffy areola. An implant alone makes it look worse. The operation releases the constricted tissue from inside, lowers the fold and reshapes the areola. Volume comes primarily from an implant; your own fat can be added if you wish. I treat tubular breasts; send photographs and I will tell you which pattern you have.
- Breast lift (mastopexy) versus augmentation. An implant adds volume; it does not lift a nipple that sits below the fold. When the nipple has dropped, the honest plan is a breast lift, with or without an implant: lift or implant after weight loss.
- Hybrid breast augmentation. A smaller implant plus fat grafting over it, explained in the section below.
- Explant, implant removal, breast implant illness. Taking implants out, with or without a lift or fat transfer to restore shape. Covered on its own page: breast implant illness and explant.
For the longer version, read the breast surgery guide.
Implant selection is measurement, not shopping
The question every patient asks first is what size. The question I answer first is what fits. Two women with the same implant can look completely different, because the implant is only one variable: the width of your breast base, the thickness of your soft tissue, the elasticity of your skin and the shape of your chest wall decide how any given implant will sit and age. In consultation we measure these, try sizers, and discuss the look you want in plain terms, natural or fuller, before translating it into a specification. A cubic centimeter number copied from social media is not a plan; the plan is the match between the device and your anatomy. If you want to understand this in more depth, I have written about how implant size should actually be chosen.
I use cohesive silicone gel implants from established manufacturers with international safety track records. Round implants suit most augmentation goals; the choice of profile, the projection of the implant relative to its width, is where most of the aesthetic fine tuning happens.
Placement and incisions
In the majority of my augmentation patients I place the implant in a dual plane, partly under the chest muscle and partly under the gland. This combines the natural upper pole coverage of a submuscular position with a more natural lower pole shape, and it is particularly forgiving in slim patients with thin tissue, where an implant placed only under the gland can show its edges over time. When the soft tissue cover is generous, a subfascial position, above the muscle but under its thin fascia, can be the right choice. I do not place implants directly under the gland.
My preferred incision is in the inframammary fold, the natural crease under the breast. It gives the most controlled access, the most predictable implant positioning, and a scar that sits hidden in the fold. Alternative incisions exist and I will discuss them honestly if your anatomy or history makes them relevant, but I will also tell you why the fold incision has become the international standard.
Hybrid augmentation: implants plus your own fat
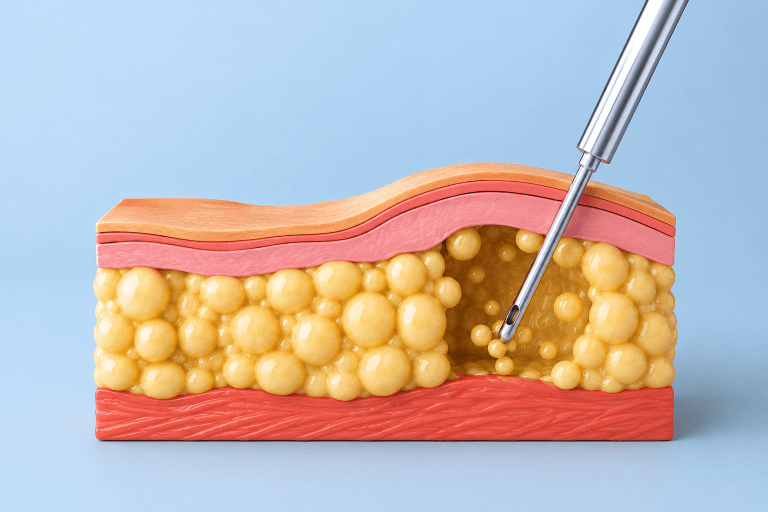
In selected patients, the most natural result comes from combining a smaller implant with structural fat grafting, using your own fat to soften the transition zones, refine the cleavage and add coverage over the implant. This composite approach is a particular interest of mine and part of my published clinical work. It is most valuable in slim patients with thin tissue, in mild asymmetries, and in post weight loss patients where the envelope needs more than volume. Not everyone is a candidate; it depends on having suitable donor fat and on realistic expectations of what fat grafting can and cannot do. You can read more about how fat behaves as a filler material on my page about fat based volume restoration.
What the process looks like for international patients
Most of my breast augmentation patients travel to Istanbul from the UK, Europe, the Gulf and the US. The process is designed around that reality. We begin with an online consultation and photographs, so that by the time you arrive, the surgical plan is already drafted and your in person examination confirms and refines it rather than starting from zero. The operation is performed under general anesthesia in a fully accredited hospital, not an office suite, and typically takes one to one and a half hours. Most patients stay one night in hospital and around five to seven days in Istanbul, with a follow up examination before flying home, and structured remote follow up afterwards. You will always know who your surgeon is, because it is me at the consultation, in the operating room, and at your follow ups.
Recovery, honestly
Early recovery from breast augmentation is more comfortable than most patients expect, particularly with dual plane placement, but it is still surgery. Expect tightness and swelling in the first week, restrictions on lifting and exercise for several weeks, and a result that settles gradually as the implants drop into their final position over two to three months. The shape you see at day five is not the shape you will live with. I have written a detailed week by week guide to breast augmentation recovery so you can plan your work, travel and family life around realistic milestones rather than optimistic ones.
The honest part: risks and lifespan
Any surgeon who presents breast augmentation as risk free is not informing you, they are selling to you. The relevant risks include capsular contracture, where the natural scar capsule around the implant tightens over years; implant malposition; rippling in thin tissue; changes in nipple sensation, usually temporary; and the general risks of any surgery such as bleeding and infection. There is also a rare lymphoma, BIA ALCL, associated principally with certain textured implant surfaces, which is exactly why implant choice and manufacturer track record matter and why we discuss them openly.
Implants are also not lifetime devices. Many patients keep the same implants for fifteen years or longer without any problem, but you should plan on the assumption that at some point in your life a revision or exchange may be needed, whether for a capsule, a change in your body, or simply a change in your preference. Building that honesty into the first operation, with conservative sizing and good tissue coverage, is what keeps future options open.
When a Boob Job Goes Wrong: Revision Breast Augmentation
Breast consultations in my practice are a mix: patients who have never had surgery, and patients with implants placed elsewhere who want a second opinion. In the second group the problems repeat, and most have a name: capsular contracture, where the scar capsule tightens and the breast turns hard, high and painful; bottoming out, where the implant slides below the fold and the nipple points upward; symmastia, where the two pockets meet in the midline; visible rippling in thin tissue, usually from a too large implant placed over the muscle; a “double bubble” when the old fold shows through below the new one; and plain size regret in either direction.
Each has a specific fix. A contracted capsule is removed and the implant exchanged, usually moving it to a dual plane position under the muscle. A fold that has dropped is rebuilt with internal sutures, sometimes with a supporting mesh, before a new implant goes in. Rippling and edge show are treated with more coverage, which means a plane change, fat grafting over the implant, or a smaller device. Size regret is the simplest and the most common: an exchange, with a lift if the skin has stretched.
Revision is more demanding than the first operation because the pocket, the capsule and the fold have all been altered. Unless there is an infection, an exposed implant or a rupture, I prefer to wait until the tissues have settled, usually six to twelve months after the previous surgery. Send photographs standing, from the front and both sides, and the implant card or operation report if you have it; knowing the implant volume, surface and plane changes the plan.
Breast Augmentation Cost in Turkey: What Shapes the Price and What Is Included
Patients searching for a boob job in Turkey are usually comparing quotes, so start with what should be inside one: the surgeon’s fee, the implants themselves with the manufacturer and warranty named, an accredited hospital rather than a clinic operating room, anesthesia given by a physician anesthesiologist, the hospital night, and structured follow up after you fly home. Prices in Istanbul are substantially lower than UK, US or German private prices for the same manufacturers and the same hospital standards, and the difference comes from local operating costs, not from the device. I do not publish a single price, because what moves the figure is specific to you:
- Implant type. Anatomical (teardrop) implants cost more than round ones, and with some manufacturers high-volume implants cost more than standard sizes.
- Augmentation alone or with a lift. A lift adds two to three hours of surgery and a different scar.
- Hybrid augmentation. Fat grafting adds a liposuction step to the same operation.
- First operation or revision. Capsule removal, pocket repair and implant exchange are planned as a separate category.
- What is combined. Breast surgery as part of a mommy makeover is quoted as one plan, not two.
I give a written quotation after reviewing your photographs and history. Every quotation is all inclusive: the surgery, the implants, the hospital stay, the anesthesia, medication, the support bra, lymphatic massage where it is part of the plan, your accommodation, airport and clinic transfers, and the follow-up visits and post-operative contact in Istanbul. Be cautious with any package whose price is only possible by removing one of those items, because that is where the saving actually comes from.
Breast Augmentation Before and After: How to Read the Photographs
Breast photographs are easy to flatter and easy to misread. Compare the same view, standing with arms relaxed, under the same light; a before photograph with the shoulders rolled forward and an after photograph with the chest lifted tells you nothing. Ask when the after photograph was taken: at four weeks the implants still sit high and the lower pole is flat, so the honest photograph is at six months or later, when they have settled. Look for a starting point like yours, in base width, existing volume and degree of sagging, rather than the most dramatic change in the set. And look at the cleavage and the side view, because that is where a too large or too wide implant shows first.
My breast augmentation results, with implant volume, profile and time since surgery, are in the before and after gallery. When you send your own photographs, I will show you cases with a similar starting point.
Frequently asked questions
Will my breasts look natural? That decision is made at the planning stage, not in the operating room. Conservative sizing relative to your base width, dual plane coverage and, where appropriate, fat grafting are what natural looks like technically.
Can I breastfeed after augmentation? In most cases yes. The inframammary approach and careful technique preserve the gland and ducts, though no surgeon can guarantee breastfeeding, including for women who have never had surgery.
How soon can I fly home? Most international patients fly five to seven days after surgery, following a check up.
I have sagging as well as volume loss. Is an implant enough? Often not, and I will tell you so directly. A lift with or without an implant may be the honest recommendation.
What if I am still losing weight on a GLP-1 medication? Then the right move is usually to wait until your weight is stable, because your breast tissue and skin envelope are still changing, and an implant chosen today may be wrong for the body you will have in six months.
How do I start? Send your questions and photographs via WhatsApp and we will begin with an online assessment.
Is a boob job in Turkey safe? The operation carries the same risks everywhere; what changes is the surgeon, the implant and the facility. Choose a board-certified plastic surgeon who performs breast surgery regularly, ask for the implant manufacturer and warranty in writing, insist on an accredited hospital, and make sure follow up after you fly home is part of the plan. I have written a separate guide on how to judge whether plastic surgery in Turkey is safe.
Round or teardrop implants? Round, for most augmentations. A round implant cannot rotate, and a natural slope comes from the plane and the profile rather than the shape of the device. If you prefer a teardrop implant, I use one; we go through the trade-offs, including rotation and the textured surface it needs, before deciding.
Do implants have to be replaced every ten years? No. There is no expiry date. Implants are exchanged when there is a reason: a capsule, a change in your body or a change in your preference. Many patients keep theirs for fifteen years or longer; an ultrasound check every few years is sensible.
Dr. Mustafa Aydınol is a plastic, reconstructive and aesthetic surgeon in Istanbul and a member of ISAPS and the Turkish Society of Plastic Reconstructive and Aesthetic Surgeons. To discuss breast augmentation in Turkey, contact the clinic on WhatsApp at +90 544 772 0772.