Tubular breasts are a developmental shape, not a disease and not something that time will fix. The base of the breast is narrow, the fold underneath sits high and tight, the lower half is short, and the areola is often wide and puffy, as if the breast tissue had been pushed forward into it. The shape appears at puberty, and many of the women who write to me have hidden it under padded bras for years.
It is also one of the few breast shapes where the obvious solution makes things worse: an implant placed under a tubular breast without releasing the constriction often exaggerates the deformity. This page explains how tubular breasts are recognized and classified, when surgery makes sense, how I correct them, what the week in Istanbul looks like, and what the honest limits are.
Tubular, Tuberous, Constricted: What Tubular Breasts Are and What They Are Not
The same shape has many names, in English and in every other language:
- Tubular or tuberous breasts. The two common English names for the same condition; “tuberous” is the term used in most medical papers.
- Constricted breast or breast base anomaly. The more precise description: the base of the breast is held in by a tight ring of fibrous tissue, so the breast grows forward instead of outward and downward.
- Puffy areola, herniated areola or “snoopy” breast. Breast tissue pushes into the areola, which becomes wide and dome shaped. Not every tubular breast has it.
- Tubuläre Brust, Schlauchbrust, Rüsselbrust. The German names. In French it is seins tubéreux, in Italian seno tuberoso, in Spanish mamas tuberosas, in Polish piersi tubularne and in Dutch tubulaire borsten.
- Tüberöz meme, tübüler meme. The Turkish names; the colloquial keçi memesi is also widely used.
A tubular breast usually shows several features at once: a narrow base, a wide gap between the breasts, a high fold, a short and flat lower half, a breast that points downward or outward, a wide or puffy areola, and a difference between the two sides.
It is not the same as small breasts. In the original classification study, only about a quarter of the operated breasts were underdeveloped in volume; almost half had a normal volume and more than a quarter were large. It is not the same as sagging, although a large tubular breast can sag as well. And the shape itself does not affect your health. It matters because of how it looks, how clothes fit and how women feel about it.
Why It Happens and How Tubular Breasts Are Classified
The cause is not known. What surgeons find is a ring of tight fibrous tissue at the base and in the lower half of the breast, which stops the breast from expanding normally during puberty, so it grows where resistance is lowest: forward, into the areola.
The classification most often used in Europe divides tubular breasts into three types:
- Type I. Only the lower inner quarter of the breast is underdeveloped. From the front the breast looks almost normal, but the lower inner part is flat. This mild form is the most common, and it is often missed.
- Type II. Both lower quarters are underdeveloped. The lower half is short, the fold sits high, and the areola often points downward.
- Type III. All four quarters are affected. The whole base is narrow and the breast has the typical tube shape, usually with a puffy areola.
A second classification adds a fourth, severe type with very little skin in the lower half. The more severe the type, the more the operation has to do.
Asymmetry is the rule rather than the exception. In a study of 375 women who came for breast surgery, most of those with asymmetric breasts also had a tubular deformity. The two breasts are often different types, and the plan has to treat them as two different breasts that should end up looking like a pair.
When Surgery Helps and When It Does Not
No exercise, cream, massage, supplement or hormone treatment changes the shape of a tubular breast, because none of them can release the constricting ring. Shaped bras camouflage it in clothes, and if the shape does not bother you, there is no medical reason to operate.
For many women it does. A study from a specialized adolescent breast center found lower self-esteem and lower emotional well-being scores in young women with tubular breasts than in women without them. Avoiding changing rooms and swimsuits, bras that never fit and discomfort in intimate relationships are legitimate reasons to consider surgery.
Surgery makes sense when breast development has finished, your weight is stable, and you understand what the operation can and cannot achieve. Patients under 18 can be operated on with the consent of a parent or legal guardian; the timing is decided at the consultation. If a pregnancy is planned soon, it is usually better to wait, because pregnancy and breastfeeding will change the breast again. And I will not place an implant alone under a clearly tubular breast, even when that is what a patient asks for.
A note for patients in Germany. Statutory health insurance pays for breast shape correction only in narrow exceptions. The assessment guideline of the Medical Service, following the Federal Social Court, does not treat breast asymmetry as an illness in the insurance sense, and in 2019 a regional social court refused coverage even for a pronounced tubular deformity of both breasts. Decisions are made case by case, so if you want to try, apply before you plan anything abroad. I have no influence on any insurer’s decision.
How I Correct Tubular Breasts
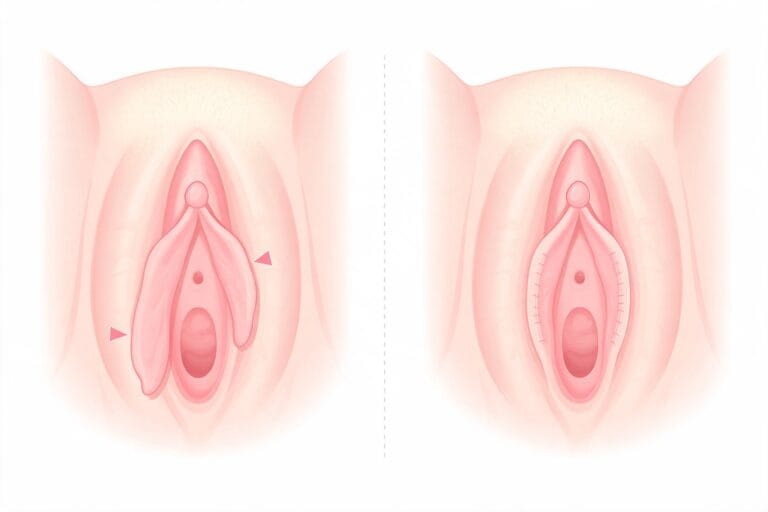
Tubular breast correction is performed in an accredited hospital under general anesthesia, with an anesthesiologist present. Whatever the type, the plan for each breast is built from the same elements:
- Releasing the constriction. The tight fibrous ring is released from inside, so the breast tissue can unfold over a wider base.
- Lowering the fold. The fold under the breast is moved down to where it should be, so the lower half becomes longer and rounder.
- Reshaping the areola. A puffy areola is reshaped, the tissue pushing into it is set back into the breast, and the areola is made smaller. The incision is placed around the areola, in the fold under the breast, or both, chosen according to the breast.
- Adding volume. Primarily with an implant. If you agree, your own fat can be added as well.
An implant without release does not correct the breast. The tight lower half holds the breast tissue up while the implant settles lower, and the old fold stays visible across the lower breast as a second crease, the double bubble. In the classification study, severe types treated with augmentation and tissue spreading alone had an unsatisfactory shape for this reason.
In tubular breasts I generally prefer a dual plane, with the implant partly under the chest muscle. Placement above the muscle, under the fascia of the chest muscle (subfascial), is the exception, used when the tissue cover is thick. The implant is chosen by measurement, as I explain in how implant size is actually chosen, and in a tubular breast the narrow base often limits how wide it can be.
Your own fat, added only if you agree, softens the lower half and the edges of the implant. Its limits are honest ones: roughly half of the grafted fat survives, so one session adds about half a cup to one cup size, and studies of fat grafting alone in tubular breasts report more operations on average than with implants. The fat is harvested by liposuction in the same operation. A smaller implant with fat grafted around it, the composite approach described on the breast augmentation page, combines the predictability of the implant with the softness of fat.
Most tubular breasts can be corrected in one operation. In severe forms with very little lower skin, I usually recommend a second fat transfer session, four months after the first. Some surgeons use a tissue expander first; I prefer the staged fat session. When a tubular breast is large or has started to sag, the correction is combined with a breast lift or a breast reduction instead of an implant.
Drains are placed in every breast operation I perform and usually come out on day two or three, based on the fluid they collect in 24 hours. Every patient wears compression stockings and calf compression during surgery, walks on the day of surgery, and receives clot prevention medication when it is indicated.
Your Week in Istanbul
- Day 0: surgery under general anesthesia, then one night in hospital. You walk the same evening.
- Days 1 to 5: at your hotel, in your support bra, with check-ups. The drains come out on day two or three. If fat was harvested, two to three lymphatic massage sessions are done in Istanbul.
- Days 5 to 7: final check and dressing the day before your flight, then you fly home. The full stay is five to seven days.
The recovery planner turns your surgery date into a day by day calendar.
Recovery After Tubular Breast Correction
The breasts feel tight and swollen for the first two weeks, and pain is usually moderate and well controlled. Your first shower is five to seven days after the drains come out. Most patients return to desk work after about a week to ten days. Wear the support bra day and night for about six weeks; it is the breasts’ only compression garment. Light cardio is possible from around week four, and chest exercises and heavy lifting from week six. If fat was also added, the bra protects the implant and the fat is not compressed further; the donor area wears its own garment for six to eight weeks in total, mainly at night after the first three weeks.
The shape changes more after a tubular correction than after a simple augmentation, because the released lower half needs time to stretch and round out. At two weeks the lower breast can still look flat and an implant can sit high; this is expected. The shape settles over three to six months, and the scars keep maturing for a year or more. My week by week guide to breast augmentation recovery covers most of the timeline.
Risks and Honest Limits
Tubular breast correction carries the risks of any breast surgery: bleeding, infection, fluid collection, changes in nipple sensation, and, with implants, capsular contracture, malposition and rippling in thin tissue. Some risks are specific to this shape: a residual double bubble, a fold that does not hold its new position, an areola that widens again under tension, and fat that partly resorbs. A systematic review of 38 studies and almost 900 patients reported an overall complication rate of 20 percent together with very high satisfaction. Not smoking is the most important thing you can do to protect healing; read my guide to smoking and surgery before you book.
Three honest limits. Perfect symmetry is not possible, especially when the two breasts started as different types; the goal is a pair that looks balanced in clothes and out of them. A tubular breast is improved, not rebuilt: your skin and tissue set the limit, and the classic studies stress the frequent need for a secondary procedure. An unplanned revision, when one is needed, is done six to twelve months after the first operation, once the tissue has settled. And breastfeeding cannot be promised: some tubular breasts have less glandular tissue, so it can be more difficult even without surgery, and surgery can affect it further.
Tubular Breast Correction Cost in Turkey: What Shapes the Price and What Is Included
I do not publish a single price, because no two tubular corrections are the same operation. What shapes the quotation:
- One breast or both. And whether the two breasts need different steps to match.
- How volume is added. The implant, and whether fat grafting is added, which adds a liposuction step.
- The skin. Whether a lift or a reduction is part of the plan.
- One step or two. When a second fat session is likely, it is discussed at the outset, not discovered later.
- What is combined. Other procedures in the same session are planned and quoted as one operation.
I give a written quotation after reviewing your photographs and history. Every quotation is all inclusive: the surgery, the hospital stay, the anesthesia, medication, the compression garment (if relevant), your accommodation, airport and clinic transfers, and the follow-up visits and post-operative contact in Istanbul.
Tubular Breasts Before and After: How to Read the Photographs
Tubular breasts are hard to judge from the front alone: compare the same posture and light, and look at the side and oblique views too. Look at four things: how wide the base is, where the fold sits, whether the lower half is round or still flat, and whether the areola is smaller and flat rather than puffy. The honest after photograph is taken at six months or later.
Many patients with tubular breasts do not want their photographs published, which I respect. My published results are in the before and after gallery, and in a video consultation I can show you more cases with a starting point like yours.
Send your photographs for an assessment. Standing photographs of your breasts without a bra, from the front, both sides and both oblique angles, with your arms down, plus your height, weight, whether one or both breasts bother you, any previous breast surgery, and whether you plan a pregnancy. Send them on WhatsApp, +90 544 772 0772, or by email, info@mustafaaydinol.com, whichever you prefer.
Frequently Asked Questions
Is a breast implant alone enough?
Not for a clearly tubular breast. Without releasing the constriction and lowering the fold, the old fold often stays visible as a double bubble. A very mild type I breast may need only small changes, which I can judge from your photographs.
Will I need one operation or two?
Most are corrected in one operation. Severe forms with very little lower skin usually need a second fat transfer session, four months after the first. I tell you at the assessment which to expect.
What if only one breast is tubular?
It is common for one breast to be more affected than the other. The plan is made for both breasts together, because the goal is a pair; if the asymmetry is significant, the other breast is treated as well.
Does German health insurance pay for tubular breast correction?
Only in narrow exceptions. German statutory insurance does not treat breast asymmetry or breast shape as an illness in the insurance sense, and a regional social court has refused coverage even for a pronounced tubular deformity of both breasts. Apply to your insurer before you plan treatment abroad.
Is tubular breast correction in Turkey safe?
The risks are the same in every country; what changes is who operates and where. Choose a board-certified plastic surgeon who treats tubular breasts regularly, an accredited hospital with an anesthesiologist, and a written plan for follow-up after you fly home. Read how to judge whether plastic surgery in Turkey is safe, and the breast surgery guide for the questions to ask any surgeon.
About the Surgeon
Dr. Mustafa Aydınol is a plastic, reconstructive and aesthetic surgeon practicing in Istanbul, a member of ISAPS and of the Turkish Society of Plastic Reconstructive and Aesthetic Surgeons. The practice holds Health Tourism Authorization from the Turkish Ministry of Health.
Sources
- Grolleau JL, Lanfrey E, Lavigne B, Chavoin JP, Costagliola M. Breast base anomalies: treatment strategy for tuberous breasts, minor deformities, and asymmetry. 37 patients, types I to III; minor forms 54 percent of operated breasts; 27 percent hypotrophic, 45 percent normal volume, 28 percent hypertrophic; 70 percent with asymmetry over 100 g; frequent need for secondary revision. Plastic and Reconstructive Surgery, 1999. DOI
- von Heimburg D, Exner K, Kruft S, Lemperle G. The tuberous breast deformity: classification and treatment. 68 tuberous breasts, four types; areolar prolapse in only 44 percent; severe types treated by augmentation and tissue spreading had an unsatisfactory shape with a “second crease” deformity. British Journal of Plastic Surgery, 1996. DOI
- DeLuca-Pytell DM, Piazza RC, Holding JC, Snyder N, Hunsicker LM, Phillips LG. The incidence of tuberous breast deformity in asymmetric and symmetric mammaplasty patients. 375 patients; 81.1 percent asymmetric, of whom 88.8 percent had a tuberous deformity; 7 percent of symmetric patients were tuberous. Plastic and Reconstructive Surgery, 2005. DOI
- Alvaro AI, Willet JW, Dounas GD, Jeeves A, Lodge M, Javed MU. A systematic review of outcomes and complications of tuberous breast surgery. 38 studies, 897 patients, mean age 24; tissue rearrangement with implant in 73 percent, fat transfer alone in 9 percent; overall complication rate 20 percent; satisfaction 99 percent. Aesthetic Surgery Journal, 2023. DOI
- Kolker AR, Collins MS. Tuberous breast deformity: classification and treatment strategy for improving consistency in aesthetic correction. 26 patients, 51 breasts; one-stage correction in 92 percent, two stages with tissue expansion in 8 percent; complication rate 7.8 percent. Plastic and Reconstructive Surgery, 2015. DOI
- Donnenfield JI, Nuzzi LC, McNamara CT, White AG, Labow BI. The impact of tuberous breast on adolescents: a cross-sectional study. 34 patients and 264 controls aged 12 to 21; lower self-esteem and lower physical and psychological quality of life scores with tuberous breasts. Plastic and Reconstructive Surgery Global Open, 2024. DOI
- Papadopoulos S, Colpaert SDM, Vidovic G, et al. Correction of the tuberous breast with fat grafting and implant: techniques, evaluation with BREAST-Q, and preliminary results. 24 patients; fat grafting needed a mean of 2.67 interventions against 1 for implants, with comparable satisfaction. Aesthetic Plastic Surgery, 2024. DOI
- Medizinischer Dienst Bund. Begutachtungsleitfaden: Plastisch-chirurgische Eingriffe an der Brust und Straffungsoperationen, assessment guideline of 2 December 2024: breast asymmetry not an illness in the statutory insurance sense (Federal Social Court); no coverage in a 2019 regional social court case of pronounced bilateral tubular deformity (LSG Nordrhein-Westfalen, L 11 KR 466/17). MD Bund